

Closed vs Open Suction Systems in Ventilated Care: What Clinical and Procurement Teams Should Know
Removing airway secretions is a routine part of caring for many patients with an artificial airway. The process itself sounds straightforward: a suction catheter is passed into the airway and negative pressure removes accumulated secretions.
The choice of suction system, however, deserves more thought.
For patients receiving mechanical ventilation, healthcare teams generally work with either an open suction system or a closed suction system. Both can remove secretions effectively, but they differ considerably in how they interact with the ventilator circuit and how they fit into critical-care workflows.
Understanding those differences is useful not only for clinicians but also for hospital procurement teams responsible for stocking respiratory consumables.
What Happens During Airway Suctioning?
Patients with an endotracheal or tracheostomy tube may not always be able to clear respiratory secretions effectively on their own.
Suctioning helps remove these secretions and maintain airway patency. It is not generally something that should happen automatically according to a fixed schedule. Current clinical guidance recommends assessing the patient for indications such as visible secretions, abnormal breath sounds or changes suggesting increased airway resistance.
The American Association for Respiratory Care also advises that suctioning should generally be performed when clinically indicated rather than simply as a routine intervention.
That makes the suction catheter part of a larger clinical decision rather than an isolated consumable.
How Does an Open Suction System Work?
With open suctioning, the healthcare professional disconnects the patient temporarily from the ventilator circuit before introducing a sterile suction catheter into the artificial airway.
After suctioning, the catheter is removed and the patient is reconnected.
The approach is well established and remains appropriate in many situations. Because the catheter enters an open airway circuit, proper sterile technique becomes particularly important.
One practical consideration is that disconnecting the ventilator temporarily interrupts the patient’s existing ventilation.
For some stable patients this may be tolerated without difficulty. For others, particularly patients requiring substantial ventilatory support, repeated circuit disconnection needs more careful consideration.
What Makes a Closed Suction System Different?
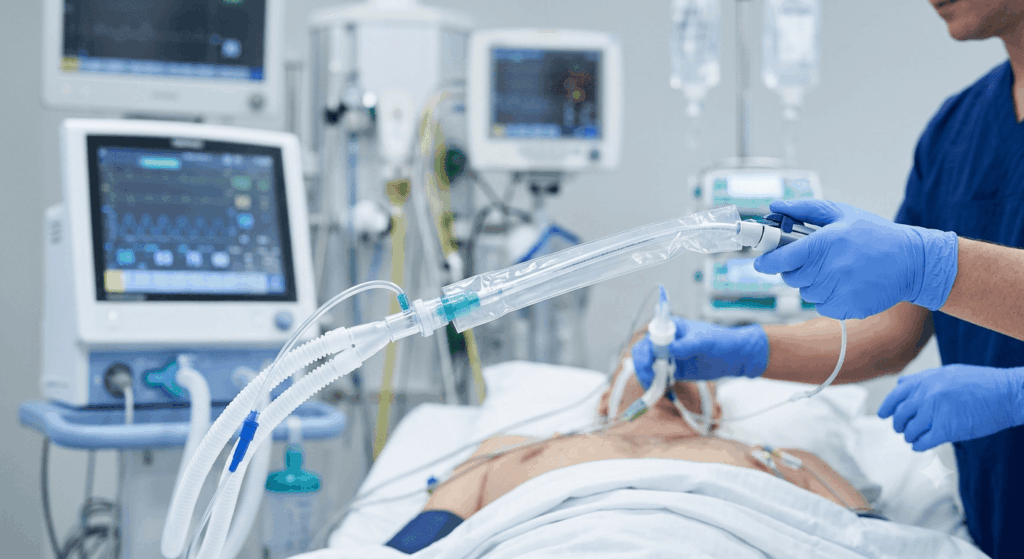
A closed suction system, sometimes called an in-line suction system, allows the suction catheter to remain incorporated within the ventilator circuit.
The clinician advances the protected catheter through the endotracheal or tracheostomy tube, removes secretions and retracts the catheter again without disconnecting the ventilator.
The main distinction is therefore not simply the catheter itself.
It is continuity of the ventilation circuit.
A closed system allows airway suctioning while mechanical ventilation continues. This can be particularly relevant where maintaining positive end-expiratory pressure or avoiding loss of lung volume is important.
Current AARC guidance states that either open or closed systems can be used safely and effectively for secretion removal in adult patients with artificial airways. Clinical circumstances determine which approach is more appropriate.
Closed vs Open Suction: The Practical Differences
Ventilator Disconnection
Open suction requires temporary separation from the ventilator circuit.
Closed suction does not.
This distinction can matter when a patient’s respiratory status makes interruption of ventilation undesirable.
Exposure of the Airway Circuit
An open technique exposes the airway and ventilator connection during suctioning.
With a closed suction catheter, the system remains connected. This may help limit environmental exposure to airway secretions and reduce unnecessary opening of the ventilator circuit.
That does not mean a closed system eliminates infection risk. Hand hygiene, device handling and adherence to infection-control protocols remain essential regardless of the system being used.
Catheter Handling
An open suction catheter is generally used for an individual suction episode according to facility procedure.
Closed suction systems are designed so that the protected catheter can remain connected to the ventilator circuit for the period specified by the manufacturer and facility protocol.
Hospitals therefore need to consider not merely the purchase price of each catheter but also how the device will actually be used within their respiratory-care workflow.
Maintaining Ventilation
This is one of the most clinically relevant differences.
Closed suction allows secretion removal while the ventilator remains connected. Earlier and current respiratory-care guidance has identified closed suction as particularly useful when avoiding circuit disconnection is important, including patients vulnerable to lung derecruitment.
Does Closed Suction Automatically Prevent Ventilator-Associated Pneumonia?
This is where healthcare content often becomes too simplistic.
Closed suction systems have infection-control advantages because the ventilation circuit does not need to be opened each time suctioning is performed. They can also reduce environmental exposure to respiratory secretions.
However, choosing a closed suction system should not be presented as a stand-alone method of preventing ventilator-associated pneumonia.
VAP risk is influenced by multiple factors, including patient condition, airway management, hand hygiene, circuit handling and broader infection-prevention practices.
Hospitals should therefore evaluate suction systems as one component of their overall respiratory-care protocol rather than expecting the device alone to solve an infection-control problem.
What Should Procurement Teams Evaluate?
When comparing closed suction catheter suppliers, healthcare organisations should look beyond the quoted unit cost.
Useful questions include:
- Which French gauge sizes and catheter lengths are available?
- Is the product sterile and intended for single-patient use according to its labelling?
- Is the catheter compatible with commonly used endotracheal and tracheostomy systems?
- How easily can clinical staff operate the suction-control mechanism?
- Is packaging clearly labelled for quick product and size identification?
- Can the manufacturer provide regulatory and quality documentation?
- Is supply reliable enough for ICU and emergency-care demand?
A device used repeatedly in critical care needs dependable manufacturing, consistent dimensions and predictable availability.
Where B+Ve® Closed Suction Catheters Fit
Omex Medical Technology manufactures a B+Ve® Closed Suction Catheter within its Anestoresp Care range.
The device is intended for tracheobronchial suctioning without disconnecting the patient from the ventilator circuit and is available in multiple sizes from 6 to 16 Fg, with 300 mm and 600 mm length options.
That range allows healthcare buyers to discuss requirements across different patient populations and clinical environments rather than treating closed suction as a single-size product.
Hospitals and distributors should always select devices according to clinical requirements, facility protocols and the manufacturer’s instructions for use.
Final Thoughts
Open and closed suction systems share the same core purpose: removing secretions from an artificial airway.
The important difference lies in how that suctioning is performed.
Open suction temporarily interrupts the ventilator circuit. Closed suction allows the clinician to remove secretions while maintaining the connection.
Neither option should be chosen simply because one sounds more advanced. Patient requirements, respiratory-support settings, infection-control procedures, staff workflow and device compatibility all need consideration.
For procurement teams, that means asking better questions before placing an order. For clinical teams, it means selecting and using the system that best fits the patient’s respiratory needs.
When those two perspectives come together, even a relatively small respiratory consumable can support a safer and more consistent critical-care workflow.
